
posted Wed, 12/02/2015 - 10:52
1289
+ 2 Pre cycle blood test. Any feedback is appreciated.
ad
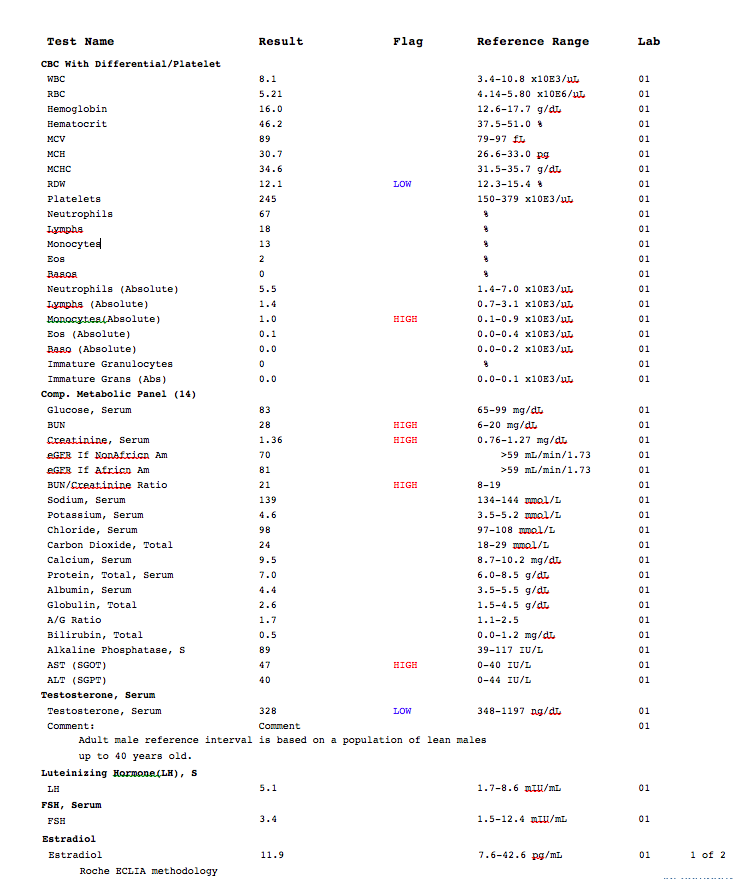
Here are my pre cycle bloods. I haven't run a cycle in about a year but I am about to start 12 weeks of GP test E@ 250mg 2x/week. I was planning on kickstarting it with TBOL again for a few weeks, but I'm a little hesitant now that I see my AST level is high.
- Bookmark
- 2
- 0
Well your BUN and creatinine clearance levels are definitely elevated. These values are related to your kidney function which is a vital aspect of maintaining your blood pressure. If your kidneys start to fail then you could go into fluid overload which puts a strain on your heart. The biggest concern isn't a heart attack it's your kidney function. Orals have to be broken down by your liver and then excreted by your kidneys. Nobody can truly pinpoint what is really going on but if you haven't run gear in a year I wouldn't even think of running any kind of oral with those kidney function values. They can be neuphrotoxic and cause even more damage. You don't want to be on the organ donation list and have to do dialysis. You need to get with your primary brother but that's just my .02$. Oh yeah and your liver enzymes could be elevated simple by good hard workouts....muscle breakdown can cause those elevated values.
I would highly highly suggest you go get your lipids checked as well both before during and after. I'm worried about you brother. I'm no doctor but I work with plenty of them and I am in the health field. Lab tech. I do a lot of blood tests a day for the hospital where I live. I would highly suggest seeing your doctor and asking about these factors I named.
What scares me here is your levels on BUN and Creatnine. Those are key signals that something's not right with the heart. Nearly every heart attack is correlated to these levels be elevated. Test will only make things worse.
Not trying to follow you around bro I just look at labs a lot as I can provide some insight. But your information is wrong. Do some more research on BUN and creatinine. Reflective of renal function like I said in the other post.
As for the OP, I wouldn't run a cycle with these labs. Your creatinine is elevated and that's worrisome. How is your blood pressure??? Are you on any meds for it??? That BUN probably isn't a big deal and reflective of your protein intake (if its high, which most guys on here it is excessively high), but kidney function in general with that creat and your gfr isn't good for someone your age.
The elevated AST is mildy elevated and like one guy said above can actually be from muscle breakdown due to exercise. It can be from a lot of things. If your primary doc isn't worried about it I wouldnt be either. But you shouldn't add any orals cuz that's just going to make it worse.
In not disagreeing with you but a lot of what you said is correct but here's the correlation between renal issues and heart problems.
Careful evaluation of the patient's history and physical examination (including signs of congestion, such as jugular venous distention [JVD]) can provide important information about the underlying cardiac abnormality in heart failure.[3] However, other studies and/or tests may be necessary to identify structural abnormalities or conditions that can lead to or exacerbate heart failure.[3]
The American College of Cardiology/American Heart Association (ACC/AHA),[3] Heart Failure Society of America (HFSA),[6, 50] and European Society of Cardiology (ESC)[5] recommend the following basic laboratory tests and studies in the initial evaluation of patients with suspected heart failure:
Complete blood count (CBC), which may indicate anemia or infection as potential causes of heart failure
Urinalysis (UA), which may reveal proteinuria, which is associated with cardiovascular disease
Serum electrolyte levels, which may be abnormal owing to causes such as fluid retention or renal dysfunction
Blood urea nitrogen (BUN) and creatinine levels, which may indicate decreased renal blood flow
Fasting blood glucose levels, because elevated levels indicate a significantly increased risk for heart failure (diabetic and nondiabetic patients)
Liver function tests (LFTs), which may show elevated liver enzyme levels and indicate liver dysfunction due to heart failure
B-type natriuretic peptide (BNP) and N-terminal pro-B-type (NT-proBNP) natriuretic peptide levels, which are increased in heart failure; these measurements are closely correlated with the NYHA heart failure classification
Electrocardiogram (ECG) (12-lead), which may reveal arrhythmias, ischemia/infarction, and coronary artery disease as possible causes of heart failure
The ACC/AHA recommendations also include obtaining a lipid profile and thyroid stimulating hormone (TSH) level.[3] These tests reveal potential cardiovascular or thyroid disease as causes of heart failure. If the clinical presentation also suggests an acute coronary syndrome, the ESC recommends obtaining levels of troponin I or T[5] ; increased troponin levels indicate injury to the myocytes and the severity of heart failure.
The ACC/AHA, HFSA, and ESC also recommend the following imaging studies and procedures[3, 5, 6] :
Chest radiography (posterior-anterior, lateral), which may show pulmonary congestion, an enlarged cardiac silhouette, or other potential causes of the patient's symptoms
2-D echocardiographic and Doppler flow ultrasonographic studies, which may reveal ventricular dysfunction and/or valvular abnormalities [61, 62]
Coronary arteriography in patients with a history of exertional angina or suspected ischemic LV dysfunction, which may reveal coronary artery disease
Maximal exercise testing with/without respiratory gas exchange and/or blood oxygen saturation, which assesses cardiac and pulmonary function with activity, the inability to walk more than short distances, and a decreased peak oxygen consumption reflect more severe disease
Other studies may be indicated in selected patients,[3] such as the following:
Screening for hemochromatosis, in which iron overload affects cardiac function
Screening for sleep-disturbed breathing, which affects neurohormonal activation
Screening for human immunodeficiency virus (HIV), which may result in heart failure from possible direct infectious effects, from disease treatment effects causing CAD, or from other causes
Testing for rheumatologic diseases, amyloidosis, or pheochromocytoma, all of which may cause cardiomyopathy
Serum and urine electrophoresis for light-chain disease
Genetic testing for at-risk patients with a first-degree relative who has been diagnosed with a cardiomyopathy leading to heart failure, which may aid in detecting early disease onset and guide treatment [27, 50]
Holter monitoring, which may reveal arrhythmias or abnormal electrical activity (eg, in patients with heart failure and a history of MI who are being considered for electrophysiologic study to document ventricular tachycardia [VT] inducibility) [5, 6]
The ESC indicates that pulmonary function testing is generally not helpful in the diagnosis of heart failure. However, it may demonstrate or exclude respiratory causes of dyspnea and help assess any pulmonary causes of dyspnea.[5]
http://emedicine.medscape.com/article/163062-workup#c1
I appreciate the reminder. Always nice to jog my memory from school. Just to give you some background on myself I work in the field and I'm very familiar with all of this. I use medscape for just about everything.
Just realized how much I posted. Didn't mean to post that while article just the top 2 paragraphs. Sorry if I came across bad. Was not my intentional what so ever. I myself work in the lab at the general hospital here where I live. It's from your posting though I can tell you know what your talking about and def have a medical background. We're all here to help each other and I learned something from you, myself. Al love brother.
No worries bro I can tell you have good intentions. Exactly, all love. Even with my background I've still learned a lot being here, and I'm sure I'll continue too.
Thanks for the feedback. I've never had an issue with blood pressure. I had a check up a few days ago for some knee pain and it was 108/70. I've never been on any meds or anything like that either. I explained what my doc told me last time in a post below about elevated levels due to creatine use and such. Do you think that could be the big contributor? Also, I had a pretty intense leg session the day prior to this blood draw which could possibly contributed with the muscle damage as well. I have annual physicals and blood work done for my job and I've never had anything come back strange other than this. I guess the only way to tell would be to get another lab done after taking a few days off of everything.
I'm not familiar with the data behind creatine use and renal function. I'd have to look into it. If this blood work isn't the normal for you I would just hold off like you said and redraw in a few weeks.
That was actually a concern of the doc when I went a few years ago. He had me do some urine labs and some more tests for my kidneys but I was told it was because I take creatine which increases creatinine during the breakdown and because of my high protein diet/muscle damage from working out a lot. I don't take creatine while on cycle but I have been taking it up until now so maybe that is playing a part in the elevated levels? Thanks for your concern man I will have it checked out to be sure.
No prob brother. I mean you def seem on the right track. You seem art about your cycling and training. Pre bloods are very important and seeing you have them done shows me your smart when it comes to aas in respect to taking care of your health. I'll send you a fr and if you have any questions along the way, or even now. Feel free to pm me.
You'll enjoy gp test!
rocketballzDamn bro. You're 29 and have really low T levels for your age. LH and FSH look good so clearly the signal to produce test is being sent to your testicles. They should be producing more test. I hope you haven't cooked your hpta. good luck man
I know man. My T levels were no different at age 23 many years before even thinking about touching anything. I went to the doc back then for lack of sex drive and issues "performing", but they didn't want to do anything because of my age and told me that they weren't low enough. I haven't been back since I started any of this about two years ago because if anything comes up weird on my labs I would be in a world of shit with my career choice. After this cycle I will probably lay low for awhile and go get checked out again. Thanks for your feedback though I appreciate it.