
+ 3 Cruising Labs 4 Weeks Post Cut
These labs are after 4 weeks off from my cutting cycle. I didn't post it, but Ferritin is at 116 ng/ml. I am very happy with seeing my fasted insulin as low as it is, but this is the lowest my z-score has ever been. I guess it's not so bad considering I pin my GH in the mornings, and I did not pin prior to getting blood work done, so this is a trough of 26 hours. I feel like I went super hard in my cut with everything I was taking, so I'm very pleased with what I see. Overall I am feeling relieved right now, and am excited to get the show on the road to grow like a weed.
Cutting Cycle
200mg Test
200mg Mast
200mg Tren (Last 8 weeks)
3IU GH
30mg Var (Last 3 weeks)
Clen 20mcg started last 8 weeks (Dosing 20mcg more every 2 weeks)
Cruise
200mg Test
3IU GH
Planned Bulk
500mg Test
140mg Eq (Just e2 control)
4IU GH - Might go to 5 or 6
Here is a link to my previous Blood Panel for more context of my cutting cycle ------> https://www.eroids.com/pics/1-month-of-tren
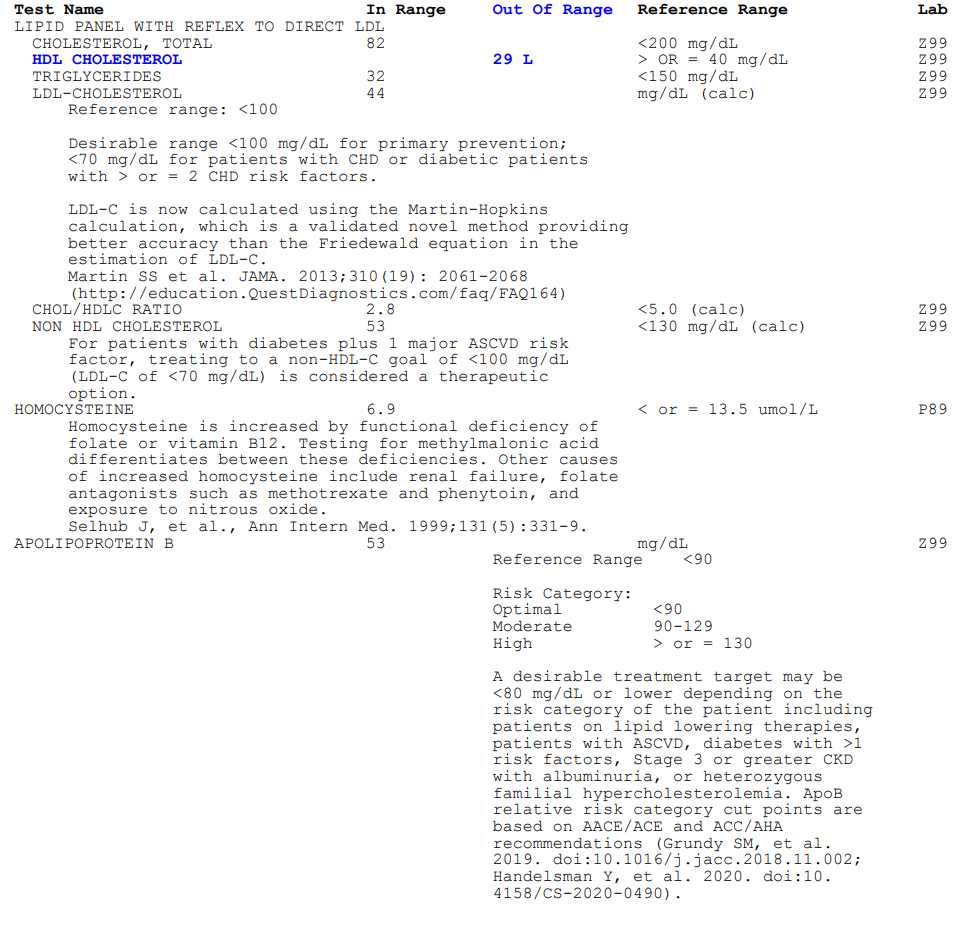
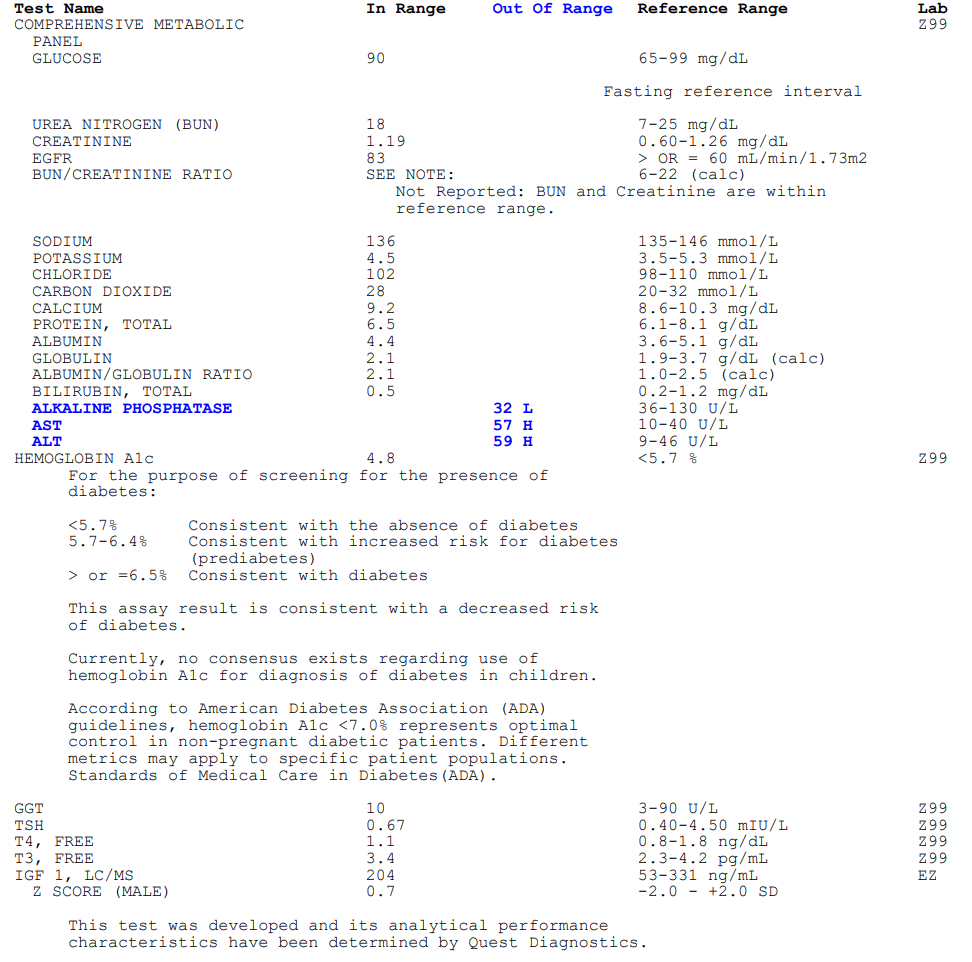
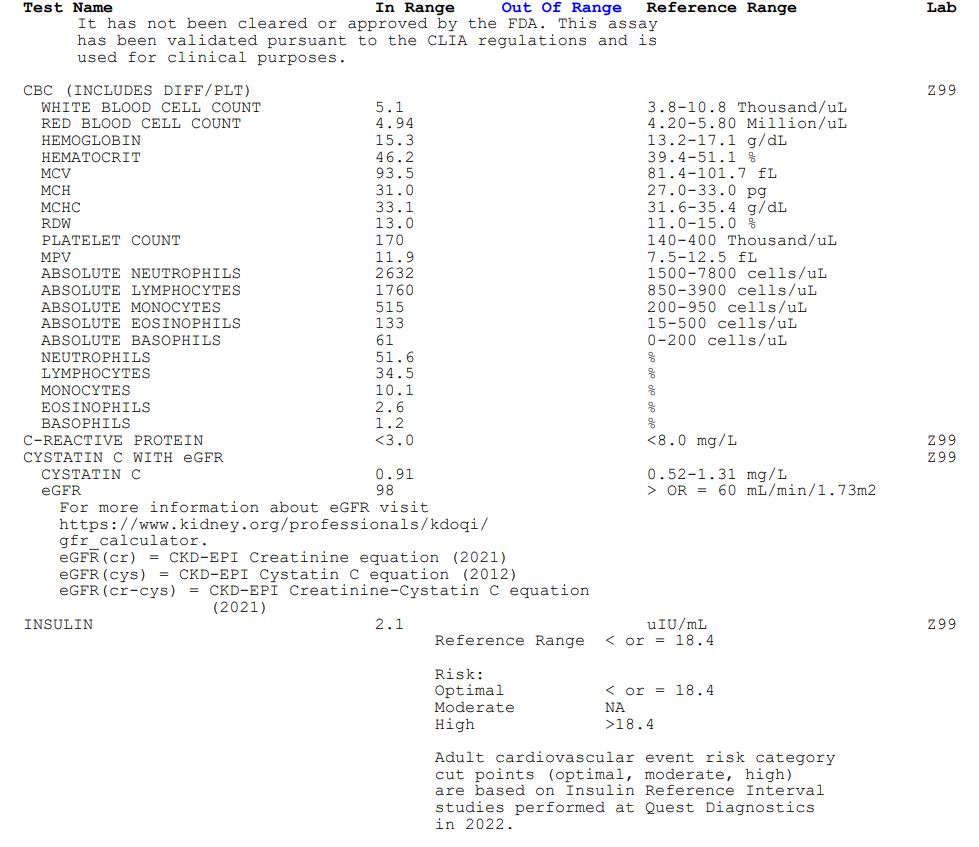
- Bookmark
- 3
- 0
Awesome man! Did you take pure anabolics hgh? How was it?
No I get my GH elsewhere.
Pristine numbers man!!
That APOB is crazy, at least you know you wont be dying of cardiovascular diseases.
And jealous of the hematocrit. Still my fucking nemesis. Going in for just hct and ferritin in the morning, hoping im still under 50 with the increased test dose
My hct keeps getting better cause I always down fluids that have electrolytes. I only drink plain water when in bed at night. I need a good low hct with going into my bulking cycle, don’t know how bad Eq is gonna skew that number. Funny you say I don’t have to worry about cardiovascular disease, cause you and myself would say something comply different about my blood work a year ago. My lipids were terrible, even though I’m eating the same and training the same. Thank god for modern medicine!
Ive got my lipids down but APOB is still high 70s with just ezetimibe. Really gonna have to consider a statin I think, even though it carries its own set of sides. But cardiovascular shit runs rampant in my family, kinda sucks knowing when I go out its likely going to be a heart attack
See I’m in the same boat, most of all the men in my family from both sides have died from a cardiovascular event. I seen I had horrible lipids on my blood panel, so I fix my diet and start working out. This is how I got into bodybuilding. I tried fixing my lipids naturally through diet and exercise for 3 years before I got on a statin, so that came first then the eztimibe came second. Wasn’t until I got on gear I said okay I need to get a statin, so in a sense gear use might of saved my life. It made me have to be that more proactive about my health.
Real shit. Without gear, I wouldnt even get all these labs done, let alone learn what they mean and how to fix them.
Thanks for posting up, bro, giving me some targets to reach for HAHA
True, I love having the knowledge of how to read blood work. I told my dad to let me see his blood work cause he said his doctor is recommending him to take Test (64 years old). My dad said “what are you gonna do with the blood work, only doctors know how to read that.” He had me laughing, but at the same time feeling bad for the average guy. Most people just don’t put in the work to learn new shit, and it’s fucking sad.
I’m gonna keep posting updates on my cycles and blood panels. I like making this website a permanent log for my personal PES use lol.
Thanks for posted
How long have you been on tren ? Stellar blood btw !
Only 8 weeks prior to the start of my cruise.
I ran tren for 12 weeks alongside anadrol and made some insane gains.
I don't really understand how and how the gains are still around.
This was all during a deficit. Nothing puts on tissue like tren and anadrol.
Was able to keep my lipis in range thanks to pitavastatin, ezetimibe, citrus bergamot.
Hdl was single digit tho.
Tren is just insane, I even made some gains in my cut using Tren as well. Half tempted to try it at the tail end of my bulk just to see what happens lmao
Try some anadrol with it man, 300 to 400 mg per week of anadrol. I promise you the gains are out of this world.
Keep that prolactin in range tho.
At 200mg of Tren per week, and taking p5p daily my prolactin was hovering around 13-14. I see what you’re saying though, Anadrol can be a bitch when exacerbating prolactin and e2 sides.
Okay so the reason tren and anadrol hits so different isn’t just that they’re both strong. It’s that they’re working through completely different pathways and not fighting each other for the same receptors.
There’s basically 3 places the androgen receptor sits on the cell. The classic one, binds the androgen, goes to the nucleus, drives gene transcription and protein synthesis, that’s the main pathway and that’s where most of your growth comes from. Then there’s one that stays on the cell surface and doesn’t do gene transcription at all, that’s the non genomic stuff. And then a subcellular one that almost nothing touches, winstrol and danazol are basically the only compounds that interact with it and nobody really knows what it’s doing.
So you can split gear into 2 classes.
Class 1 works through the classic AR. Test (though test is the only one with fully mixed activity, genomic and non genomic both), EQ, primo, nandrolone, tren. Masteron is unclear, it’s barely been studied.
Class 2 has little or no AR affinity and works through other routes. Anadrol (literally no known affinity for the androgen receptor), dbol, winstrol.
Here’s why stacking within a class does nothing much. You add EQ to your test, that’s one plus one on the same pathway. You’re just hitting the AR over and over with the same key. You’re not getting anything you couldn’t have got by just running more test, and you’re probably getting less because they’re competing for the same finite pool of receptors. Same deal adding primo or mast. There’s very little primo does that test doesn’t already do.
Now tren and anadrol is a different thing entirely because they’re the strongest compound in each class and they’re not stepping on each other.
Tren is the most potent class 1 there is. Lower KD value, meaning it binds the AR way tighter than test, EQ, Mast or Primo and it doesn’t get converted down into weaker metabolites the way test does. Plus it’s strongly anti catabolic and partitions nutrients, which is exactly why it works so well in a deficit where everything else struggles.
Anadrol has no known AR affinity at all. It’s working through non AR routes including direct estrogen receptor activation. So it’s not competing with the tren for receptor space, it’s doing its thing somewhere else completely.
So you end up with two separate pathways maxed at the same time instead of one saturated pathway. 50 mg of anadrol plus 50 mg of tren does more than 100 mg of either on its own. Anyone who’s run both together knows the growth is noticeably different to adding primo to tren.
If you wanted to cover every base it’d be test as the base, tren for the classic AR, anadrol for the non AR, winstrol for the subcellular one.
One more thing worth knowing. New androgen receptors get made during the translation stage of protein synthesis, and translation is the one stage that actually needs energy. So if you’re in a deficit you’re limiting how many new AR you make. Tren might partly outwork that, which is another reason it earns its spot in a cutting stack when other stuff doesn’t.
Now the caveats because I’m not going to pretend this is settled science.
The class 1 and 2 thing is dated and oversimplified. Real androgen signalling is a spectrum of binding affinities and a bunch of different non genomic mechanisms, not two neat boxes. The DHT derived orals especially don’t fit cleanly.
And the synergy being real doesn’t mean you should run it. To get it you need the harsh orals, and the potency and the toxicity come from the same place. That’s competitor logic. For most people test, primo and GH covers what you actually need. I ran tren and anadrol, it worked exactly like the theory says, and I’m not doing it again.
Damn bro you just dropped a bombshell of interesting information on me. I read through the whole thing, but might need to come back to reread it a few more times to really absorb all of it lol. Thanks for that, and I’m sure plenty of others will find it interesting as well.
Thanks bro but this ain't my discovery, this is just a summary of the anabolic roundtable.
Here is the link : https://youtu.be/rJJZQdMcJiQ?list=PLZ-LZCd8mxnfmT4gbZmbpGNDluw81eC26
They start talking about genomic and non-genomic AAS at around 01:40:00.
Thanks brother man, I’m gonna have to check this out later.
Absolutely spiked my prolactin to hell, started getting ichy nipples. Thankfully I was prepared. Even though I was prepared l-tyrosine, p5p, masteron on hand and finally caber. The nipples sensitivity continued even when prolactin was back in range.
What completely stopped all of the sides is tamoxifen 20 mg split morning evening.
What's your cholesterol management protocol?
I'd say your cut has your primed and ready to grow! Fasting insulin looks great, along with hba1c
Just 10mg Atorvastatin and 10mg Ezetimibe daily every night before bed.